
- Define public health, public health nutrition, public nutrition and community in the book’s words
- Explain why malnutrition in India is serious, the double burden of malnutrition and the factors related to undernutrition (Fig. 3.1)
- Tell apart PEM, underweight, stunting, wasting, marasmus and kwashiorkor
- Write the causes, signs and consequences of iron-deficiency anemia (IDA), vitamin A deficiency (VAD) and iodine deficiency disorders (IDD)
- Describe POSHAN Abhiyaan, food-based and medicinal strategies, the nutrition programmes of India and the three levels of health care
- Explain the role of a public nutritionist, the career avenues and the practical on supplementary foods
1 Introduction: What Does “Public” Add?
- In Class XI you studied the basic ideas of nutrition and health, physical fitness and wellness
- Good nutrition is the foundation and cornerstone of health
- The definition of health you know comes from the World Health Organisation (WHO); adding the word “public” shifts the focus from one person to the whole population
The concept of public health refers to the collective action taken by society to protect and promote the health of the whole populations.
The mission in public health nutrition is to prevent both undernutrition and overnutrition and to maintain optimal nutritional status of the population.
1.1 Undernutrition and overnutrition
Undernutrition
- The body gets less food or fewer nutrients than it needs
- Examples in this chapter: low birth weight, stunting, anemia
Overnutrition
- Taking in more energy, sugar, fat and salt than the body needs
- Examples in this chapter: overweight, obesity, diabetes
2 Significance: Why Focus on Public Nutrition?
2.1 The numbers for India
- Low birth weight may have adverse effects throughout the growing years and even in adult life; it may even lead to child mortality (death in childhood)
- Growth retardation (growth slower than normal) is widespread among pre-schoolers from socio-economically disadvantaged families
- A large proportion of children (and adults) suffer from micronutrient deficiencies of varying severity, also known as hidden hunger
- The micronutrients of most concern: iron, zinc, vitamin A, vitamin C, vitamin D, iodine, folic acid and B12
2.2 What malnutrition does, and what it costs
- The costs of malnutrition are very high
- Experts estimate that productivity losses are more than 10 per cent of lifetime earnings for individuals
- For the nation, the loss is 2-3 percent of gross domestic product (GDP)
- So if we tackle malnutrition, we help India to develop, grow economically and become a powerful nation
2.3 Overnutrition is rising
India mostly faces undernutrition, but overnutrition is also on the rise, because over the years large numbers of people have changed their dietary patterns and lifestyles.
Change in lifestyle
- People have become more sedentary (sitting most of the day)
- They rely on faster means of transportation
- They walk less and do less physical activity
- In large cities even children do not play enough outdoor games
Change in diet
- Food choices have become less “healthy”
- More: processed foods, fast foods, snacks, western type foods (burgers, pizzas, biscuits, chocolates, cakes, pastries, soft drinks), even Indian mithais and samosas
- These are high in energy, sugar, fat, salt and low in other nutrients and fibre
- Less: whole grains, pulses, vegetables and fruits
- These diseases are non-communicable (they do not spread from person to person)
- They harm physical health, lower the quality of life and add to the financial burden
India is said to face “the double burden of malnutrition”, i.e., the coexistence of both undernutrition and overnutrition.
2.4 The challenge of communicable diseases
- Communicable diseases like smallpox have been controlled
- But newer ones like HIV/AIDS and old ones like tuberculosis, hepatitis and malaria are increasing
- The consequences are far worse for those who are not optimally nourished: the undernourished, and those with lower immunity due to obesity, diabetes, HIV/AIDS, etc.
- This is a challenge for doctors, nutritionists and the government in treatment, control and prevention
- So there is a tremendous need for a trained cadre of public health professionals, including public health nutritionists
3 Basic Concepts
3.1 What is public health nutrition?
Public health nutrition is the field of study that is concerned with promotion of good health through prevention of nutrition-related illnesses / problems in the population, and the government policies and programmes that are aimed at solving these problems.
- Public health nutritionists use large scale, organised and multidisciplinary (drawing on many subjects) approaches
- They deal with problems that affect a large number of people for whom group action is necessary
- The field is built on the foundations of biological and social sciences
- It is a special body of knowledge derived from the nutritional, biological, behavioural, social and managerial sciences
Clinical nutrition and dietetics
- General knowledge (not in the book): the main focus is one person or patient; it is the subject of Chapter 2 of this book
Public health nutrition
- Addresses problems of the community / public, especially the vulnerable groups
- Works through government policies and programmes
Public nutrition can also be described as “the art and science of promoting health and preventing diseases, prolonging life, through the organised efforts/action of society.”
A community is a specific group of people who share common characteristics, e.g. a common language, exposed to similar conditions, common lifestyle or the same health problem.
3.2 The work of a public nutrition professional
Any professional in public nutrition has to promote good nutrition and/or prevent nutritional problems. The steps are:
3.3 Roots of nutritional problems: poverty and other factors
- Nutritional problems are not linked to food alone but to many interacting/interrelated factors at various levels (Fig. 3.1)
- Poverty is often the underlying cause
- The situation becomes worse when many families do not have access to basic amenities
- Rural households have less access to toilets; poor sanitation results in loss of work days and further economic loss
- A considerable proportion of the population does not have safe drinking water; working days are lost each year due to water borne diseases
Economic factors
Availability of financial resources
Agricultural policy
Production and price of various food stuffs
Health care
Facilities/services, their availability and access
Government policies
and political will
Socio-cultural factors
Social and cultural conditions

- Basic cause 2 also includes: the status of women, allocation of funds for programmes to solve the problems, environmental degradation and biodiversity
- “Organisational” resources means the existence of services and the way they are operated and controlled
- Underlying cause 5 in full: inadequate and/or inappropriate knowledge, and discrimination against women, elderly and girl child
In a situation question (“young children fall ill often and show poor growth”), if household-level causes are asked, write two from these six, e.g. poor water/sanitation and hygiene, poor maternal and child care practices.
4 Nutritional Problems in India
4.1 (a) Protein-Energy Malnutrition (PEM)
- Found in every society, even in developed and industrialised countries, though the numbers there are fewer than in developing countries
- Cause: inadequate food intake vis-a-vis the requirements, i.e., insufficient intake of the macronutrients (energy and protein)
- Children are at greatest risk; PEM also occurs in adults, especially the elderly, and in some diseases, e.g. T.B., AIDS
- It is assessed by anthropometric measurements (body measurements: weight, height, head-chest circumference, etc.)
A person is said to be underweight when his/her body weight is less than adequate for his/her age.
Stunting (short stature) is said to be present when the height is less than adequate for age.
When weight is not adequate relative to height, it is termed “wasting”.
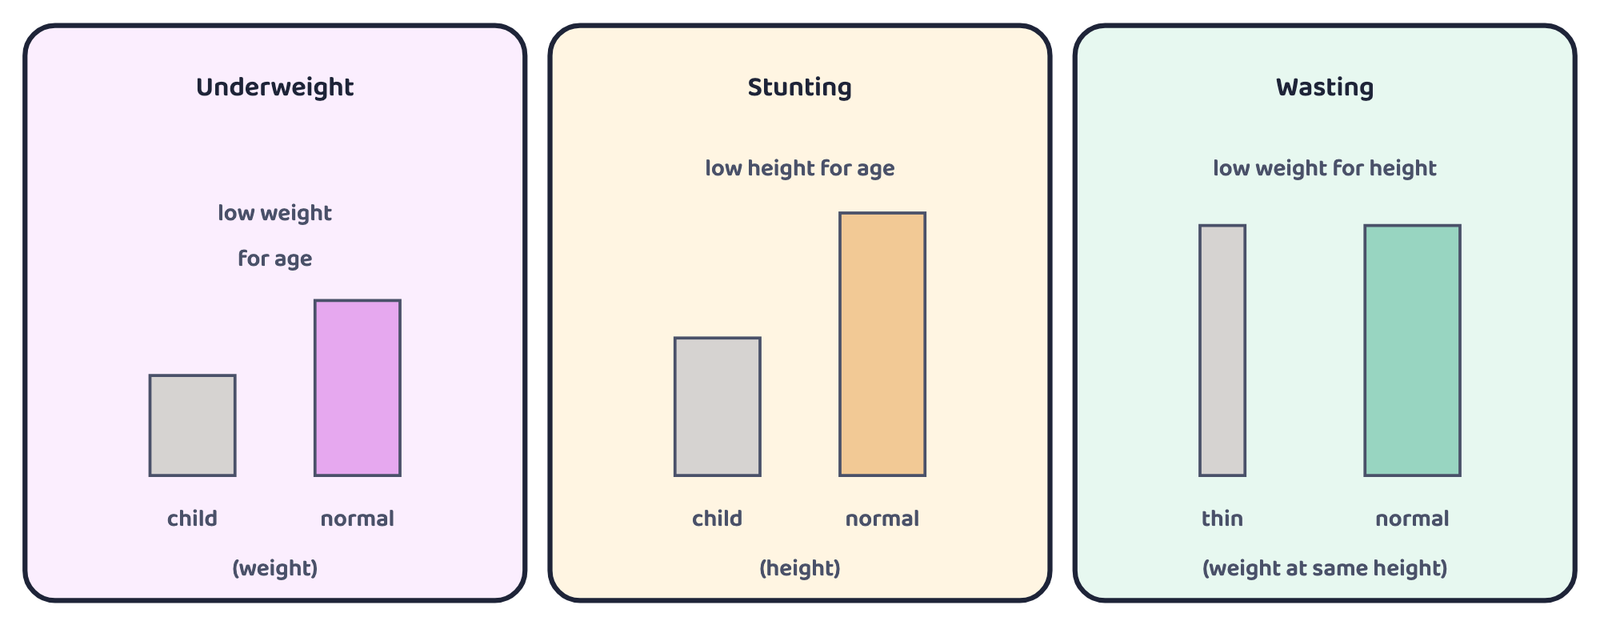
“Low weight for height” is wasting, not stunting. In stunting, height is compared with age.
Severe undernutrition due to deficiency of food and energy is termed “marasmus”.
Severe undernutrition caused by protein deficiency is termed “kwashiorkor”.
- If the diet is deficient in energy and protein, it is also likely to have too little of other nutrients, especially micronutrients, viz. minerals and vitamins
The term “hidden hunger” is used to refer to micronutrient deficiency (the stomach may feel full, but the body is short of minerals and vitamins).
Of major public health concern
- Iron
- Vitamin A
- Iodine
- Zinc
Of growing concern
- Vitamin B12, folic acid
- Calcium, vitamin D
- Riboflavin
4.3 (i) Iron-deficiency anemia (IDA)
- The most common nutritional disorder in the world; prevalent in both developed and developing countries
- Vulnerable groups: women in child-bearing age, adolescent girls, pregnant women and school age children
- IDA occurs when hemoglobin production is considerably reduced, resulting in low levels of hemoglobin in blood
- Symptoms depend on the rate of fall in hemoglobin
- Hemoglobin carries oxygen in the body, so any physical exertion leads to shortness of breath (breathlessness on slight exertion)
- The person complains of fatigue and may feel lethargic (dull, without energy)
Visible signs (paleness)
General pallor; paleness of the conjunctiva of eyes, tongue, nail beds and soft palate
Effect on children
Cognitive functions are adversely affected: attention span, memory, concentration
4.4 (ii) Vitamin A deficiency (VAD)
- Vitamin A is necessary for: healthy epithelium (the lining tissue of the body), normal vision, growth and immunity
- Its deficiency results in night blindness (not seeing in dim light)
- This progresses to complete blindness if corrective measures are not taken
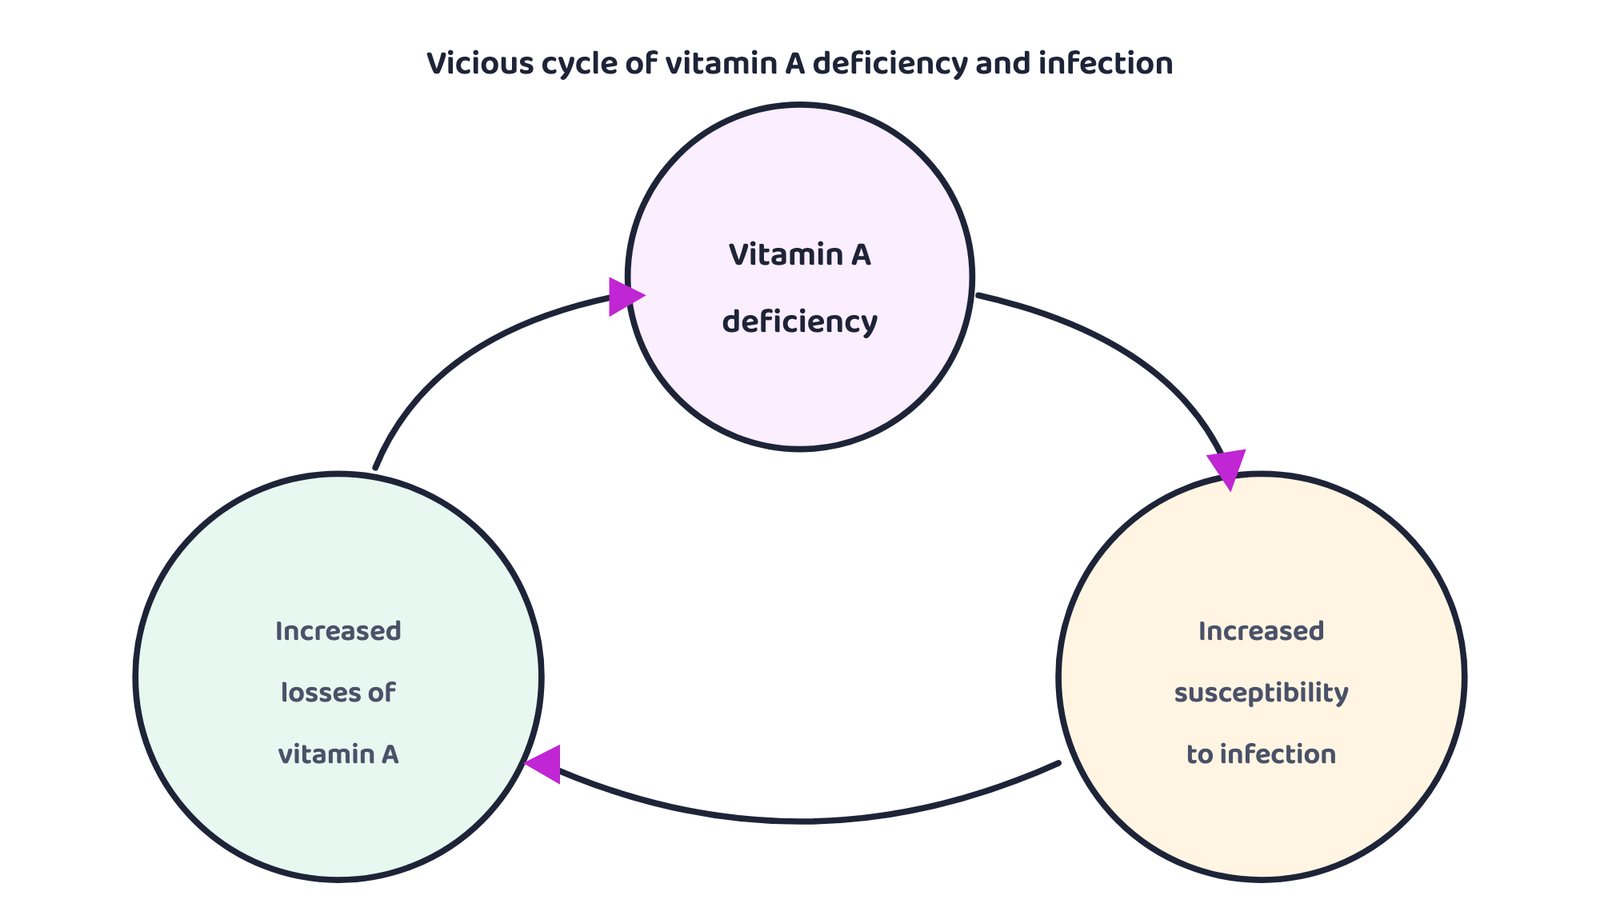
- There is also less resistance to infection, and growth may be adversely affected
- Vitamin A deficiency is the most common cause of childhood blindness
- The book’s photo caption: yellow, green and orange fruits and vegetables are good sources of vitamin A
- Other photos in the book (source: SIGHT and LIFE, Basel, Switzerland): victims of PEM and micronutrient deficiency, providing nutritious food, a child with vitamin A deficiency, a vitamin A deficiency picture of the eye, iron and folic acid drops, weighing of a child, counselling with mothers
4.5 (iii) Iodine deficiency disorders (IDD)
- Iodine is required for normal mental and physical growth and development
- IDD is an ecological phenomenon (a problem of the environment), largely due to deficiency of iodine in the soil
- The term refers to a spectrum of disabling conditions that affect health from fetal life through adulthood, due to inadequate dietary intake of iodine
- Deficiency of iodine results in an insufficient amount of thyroid hormone, which is synthesised (made) by the thyroid gland
- An enlarged thyroid, known as goitre, is the most common manifestation (visible form) of iodine deficiency in adults
- In children it manifests as cretinism
- Iodine deficiency during pregnancy causes mental retardation and congenital abnormalities (defects present at birth) of the fetus; this effect is irreversible (cannot be undone)
| States in India where IDD is common (as given in the book) | |
|---|---|
| Himalayan belt | Jammu and Kashmir to Arunachal Pradesh |
| Other states | Andhra Pradesh, Karnataka, Kerala, Maharashtra and Madhya Pradesh |
4.6 At a glance: the three micronutrient deficiencies
| Deficiency | Cause / what falls | Vulnerable groups | Signs / consequences | Measures named in the book |
|---|---|---|---|---|
| IDA Iron-deficiency anemia |
Iron deficiency; hemoglobin production reduced | Women in child-bearing age, adolescent girls, pregnant women, school age children | Breathlessness, fatigue, pallor; children’s attention and memory affected | Iron and folic acid supplements (photo: iron and folic acid drops); National Nutritional Anemia Prophylaxis programme |
| VAD Vitamin A deficiency |
Vitamin A deficiency | Children (childhood blindness) | Night blindness → complete blindness; more infection; poor growth | Yellow, green, orange fruits and vegetables; vitamin A supplementation; National Prophylaxis Programme for Prevention of Blindness due to Vitamin A deficiency |
| IDD Iodine deficiency disorders |
Iodine deficiency in soil; thyroid hormone falls | Fetal life through adulthood; pregnant women | Goitre, cretinism in children, mental retardation and congenital abnormalities of the fetus | Salt fortified with iodine; National Iodine Deficiency Disorder Control Programme |
5 Strategies / Interventions to Tackle Nutritional Problems
“The problem of malnutrition is a matter of national shame …… I appeal to the nation to resolve and work hard to eradicate malnutrition in 5 years”.
Former Prime Minister Dr. Manmohan Singh, in one of his speeches (quoted in the book)
- A multi-disciplinary approach is needed to solve nutritional problems, and the government is making considerable efforts
5.1 POSHAN Abhiyaan
- POSHAN Abhiyaan = the PM’s Overarching Scheme for Holistic Nutrition
- Launched in Jhunjhunu, Rajasthan in March 2018
- It targets stunting, under-nutrition, anaemia (among young children, women and adolescent girls) and “low birth rate” (the book’s wording)
- It is meant to monitor and review the implementation of all such schemes
- Its large component is the gradual scaling-up (step-by-step expansion) of interventions to all districts of the country by 2022
- Through a robust multi-ministerial convergence mechanism (many ministries working together), it strives to create synergy
Direct short term interventions
- (a) Integrated Child Development Services (ICDS) to cover all vulnerable children aged 0-6 years and all pregnant and lactating mothers
- (b) Fortification of essential foods (salt fortified with iodine)
- (c) Production and popularisation of low cost nutritious foods from indigenous and locally available raw material, by involving women
- (d) Control of micronutrient deficiencies (iron, vitamin A, folic acid, iodine) among children, pregnant women and nursing mothers, by supplementing these nutrients, distributing free tablets, etc.
Indirect policy instruments (long term)
- Long term strategies through indirect institutional or structural changes
- (a) Ensuring food security, i.e., improving availability of food
- (b) Improvement in dietary patterns by ensuring availability of nutritionally rich foods
- (c) Poverty alleviation for rural and urban poor
- Employment generation schemes and the public distribution system
- Implementing land reforms; improving health and family welfare
- Prevention of food adulteration; involvement of media
- Basic nutrition and knowledge; monitoring of nutrition programmes
- Improvement of the status of women, education and literacy; community participation
5.2 Classification of strategies
Diet or food-based strategies are preventive and comprehensive strategies that use food as a tool to overcome nutritional deficiencies.
- They prevent micronutrient deficiencies by increasing the availability and consumption of micronutrient-rich foods
- One of the important advantages: the strategy is sustainable and has long-term benefits
- They are cost-effective (more benefit for less money)
- They can be adapted to different cultural and dietary traditions
- Very importantly, they carry no risk of overdose or toxicity (poisoning), which may happen with the nutrient-based / medicinal approach
Dietary diversification and modification
Eating a wider variety of foods
Horticulture interventions
e.g., home gardening
Nutrition and health education
Teaching people what and how to eat
Food fortification
Fortifying food with nutrients
In this approach nutrient supplements are given to vulnerable groups, i.e., those who are at risk of deficiency and those who have deficiency.
- It is a short term strategy, used in India particularly for vitamin A, iron and folic acid
- Supplementation programmes are often expensive, and there may be problems of coverage (reaching everyone who needs them)
- Key target groups are different for various nutrients
The book: the long-term goal should be to shift away from supplementation towards food-based approaches.
5.3 Table 3.1: Different interventions for tackling malnutrition
| Intervention | Appropriate for | Advantages | Challenges / Disadvantages |
|---|---|---|---|
| Medicinal or nutrient based | |||
| Nutrient supplementation | Therapeutic treatment; prevention programmes for specific nutrient and specific target groups | Timely; sustainability | More costly than other measures; narrow scope of coverage |
| Food based or diet based strategies | |||
| Fortification (fortifying food with nutrients) |
Prevention (universal / for all) | Highly cost-effective; wide coverage; sustainable | Requires research; participation of food industry; does not lead to awareness in the population about the importance of nutrition and nutrients; does not lead to long-term dietary/behavioral changes |
| Dietary diversification | Prevention (universal / for all) | Highly cost-effective; wide coverage; sustainable; provides many micronutrients simultaneously; improves food security | Requires changes in eating behaviour; requires economic development to be feasible; requires change in agricultural policies |
Adapted from: Public Nutrition (Course Material) published by Indira Gandhi Open University (as printed in the book)
For “one advantage and two drawbacks of food-based strategy”, take the advantage from the text (sustainable, cost-effective, no risk of toxicity) and the drawbacks from the last column of Table 3.1 (e.g. requires changes in eating behaviour; does not lead to awareness about nutrition).
6 Nutrition Programmes Operating in India
| # | Type of programme | Examples given in the book |
|---|---|---|
| 1 | ICDS (Integrated Child Development Services) | An outreach programme for early childhood care and development, covering pregnant and nursing mothers, infants and young children up to 6 years |
| 2 | Nutrient Deficiency Control programmes | National Prophylaxis Programme for Prevention of Blindness due to Vitamin A deficiency; National Nutritional Anemia Prophylaxis programme; National Iodine Deficiency Disorder Control Programme |
| 3 | Food Supplementation Programmes | The Mid-Day Meal Programme |
| 4 | Food Security Programmes | Public Distribution System, Antodaya Anna Yojana, Annapurna Scheme, National Food for Work Programme |
| 5 | Self-employment and wage employment schemes | These are social safety net programmes |
The Mid-Day Meal is a food supplementation programme, not a food security programme. The Public Distribution System, Antodaya and Annapurna are food security programmes. “Prophylaxis” means prevention.
7 Health Care
- Health is a fundamental human right; it is the responsibility of the government to provide adequate health care to the citizens
- Health care is not just medical care
- It includes a multitude of services that help to promote, maintain, monitor or restore health
- In India, health care is provided at three levels: primary, secondary and tertiary
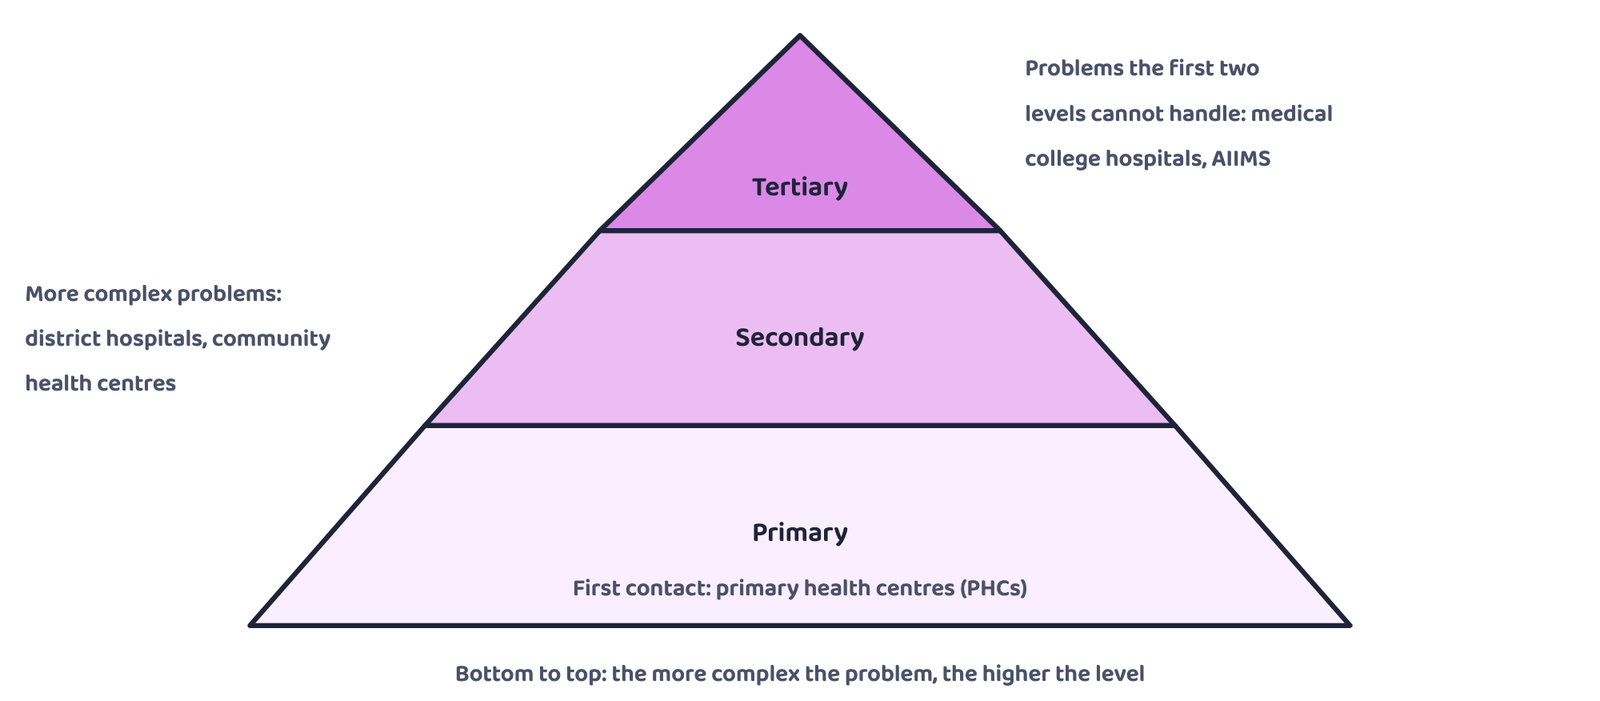
| Level | What it does | Where the service is given |
|---|---|---|
| Primary | The first level of contact of the individual, family or community with the health system | A network of primary health centres (PHCs) |
| Secondary | More complex health problems are resolved | District hospitals and community health centres; community health centres function as the first referral level |
| Tertiary | The third and highest level; the more complex problems that cannot be dealt with at the first two levels | Medical college hospitals, regional hospitals, specialised hospitals and All-India Institutes of Medical Sciences |
8 Scope: Role of the Public Nutritionist
- Nutrition is an important determinant of health
- The changing health scenario globally has increased the challenges for public nutritionists
- The public nutritionist is also called a community nutritionist
- A well-trained public nutritionist is eminently suited to take part in all the strategies of health promotion and prevention
Above: the eight key areas in which a community nutritionist is trained
| # | Where a community nutritionist can work |
|---|---|
| (a) | Outreach programmes of hospitals for prevention, promotion and education |
| (b) | The national Integrated Child Development Services, at different levels based on qualifications and expertise |
| (c) | At the government level as consultants, advisors, or in policy making committees |
| (d) | Developmental programmes of government, voluntary organisations, NGOs and international organisations like UNICEF, USAID, GAIN, Nutrition International, TATA Trust, IFPRI, and many other national and regional organisations |
| (e) | Organisations running large scale feeding programmes for young children, school children, adolescents, pregnant and lactating mothers, the elderly and challenged individuals |
| (f) | As nutritionists or school health counsellors in school health programmes |
| (g) | Corporate CSR programmes dealing with food and nutrition security of vulnerable groups |
- Besides this, there are avenues in teaching, research and entrepreneurship
- And with agencies that develop communication materials and educational packages
8.1 Career avenues
Hospitals
Community nutritionist in PSM departments of hospitals
Government programmes
Nutrition programmes, e.g., ICDS, Food and Nutrition Board
Voluntary organisations
Regional, national and international, as nutritionists
Consultants
Working as consultants
Schools and industries
Nutritionists or counselors for schools, industries, etc.
Teaching
Teaching and academics
Research
Research work
PSM = Preventive and Social Medicine (general knowledge, the book uses only the short form)
9 Practicals and Activities
Theme: Development and preparation of supplementary foods for nutrition programmes.
Purpose: gives insight into planning, costing and preparing supplementary foods for preschoolers within a given budget.
- Task 1: obtain the prices of commonly consumed, locally available foods
- Task 2: plan low-cost recipes of supplementary food for preschoolers attending an Anganwadi
- Task 3: prepare the selected recipes
- Task 4: evaluate the prepared recipes
| Group | Recipes that are good sources of |
|---|---|
| A | Energy and protein |
| B | Iron |
| C | Vitamin A or beta carotene |
| D | Calcium |
- Students are divided into 4 groups; each group plans 2 recipes and calculates the cost using the price list
- Plans are made for 5 servings; the teacher gives a cost limit (not more than ₹5 per serving)
- Students do not have to calculate nutritive values
- Each group identifies locally available food sources of its nutrient; the teacher checks the plans and selects one suitable recipe
- The product is prepared in class and evaluated for (a) serving size (b) cost (c) suitability for preschoolers (d) appearance (e) taste (f) acceptability by children
- Observations and comments are recorded and suggestions given for improvement
CBSE: plan a menu for a school canteen or the mid-day meal in school for a week. UP Board: a weekly menu with at least four sweet and four savoury dishes, keeping nutrition and safety in mind, using milk, green and fresh vegetables, fruit, chhena and khoya.
General knowledge (not in the book): while planning, include every day a cereal + pulse (energy, protein), green leafy vegetables (iron), yellow-orange fruits and vegetables (vitamin A), milk/curd/chhena (calcium), and iodised salt.
| Day | Sample menu (change it to suit your region) |
|---|---|
| Monday | Roti, dal, spinach-potato sabzi, banana |
| Tuesday | Rice, rajma, carrot salad; jaggery-chana (sweet) |
| Wednesday | Missi roti, lauki-chana dal, curd |
| Thursday | Vegetable pulao, soya chunks, papaya; kheer (sweet) |
| Friday | Moong dal chilla, green chutney, seasonal fruit |
| Saturday | Vegetable daliya khichdi; chhena or khoya sweet (sweet); peanut-jaggery laddoo (sweet) |
- Activity 1: visit an Anganwadi (ICDS centre), talk to the supervisor or sevika, watch the food distribution, prepare a PowerPoint presentation
- Activity 2: an interactive session on undernutrition and its causes with a medical officer / health in-charge of a PSM dept, PHC or Municipal Corporation
- Activity 3: a school exhibition on nutritional problems in India, their causes, vulnerable groups and simple preventive measures
- Activity 4: visit the websites of WHO, UNICEF, Poshan Abhiyaan, the Ministry of Health and Family Welfare and the Ministry of Women and Child Development
How to do each activity is explained in the NCERT Solutions post.
Key Terms (from the book): nutritional status, undernutrition, malnutrition, public health, public nutrition, nutrition programmes, community health.
- Public health = collective action of society; mission of public health nutrition = prevent undernutrition AND overnutrition
- At least 50% of under-five child deaths: malnutrition; one-fifth of infants low birth weight (below 2500 g)
- Cost: over 10% of lifetime earnings, 2-3% of GDP
- Double burden = undernutrition + overnutrition; overnutrition leads to non-communicable diseases (hypertension, heart disease, diabetes, cancer, arthritis)
- Fig. 3.1: basic → underlying household (6) → immediate individual (diet, disease) → malnutrition, disability, death; poverty is often the root
- Underweight = weight/age; stunting = height/age; wasting = weight/height; marasmus = food and energy, kwashiorkor = protein
- Hidden hunger: iron, vitamin A, iodine, zinc; IDA = most common nutritional disorder in the world
- VAD: night blindness → blindness, vicious cycle with infection; IDD: soil, goitre, cretinism, 13% affected, about 30% at risk
- POSHAN Abhiyaan: March 2018, Jhunjhunu (Rajasthan); MWCD 315 → 235 → remaining districts; convergence
- Food-based (sustainable, cost-effective, no toxicity) vs medicinal (short term, expensive; vitamin A, iron, folic acid)
- Programmes: ICDS · deficiency control (vitamin A, anemia, IDD) · Mid-Day Meal · PDS, Antodaya, Annapurna, Food for Work · employment schemes
- Health care: primary (PHC) · secondary (district hospital, CHC = first referral level) · tertiary (medical college, AIIMS)
- Can I write the definitions of underweight, stunting and wasting without mixing them up?
- Can I list the six household-level causes in Fig. 3.1?
- Can I write the consequences of IDA and IDD separately?
- Can I give four differences between food-based and medicinal approaches?
- Can I name the five types of nutrition programmes with examples, and the three levels of health care?